Master sugar substitutes for Type 1 Diabetes. Learn how sucralose, aspartame, and sugar alcohols affect blood glucose, and learn to decode packaging labels.
The Complete Guide to Artificial Sweeteners in Type 1 Diabetes: Sugar Substitutes and Food Labels
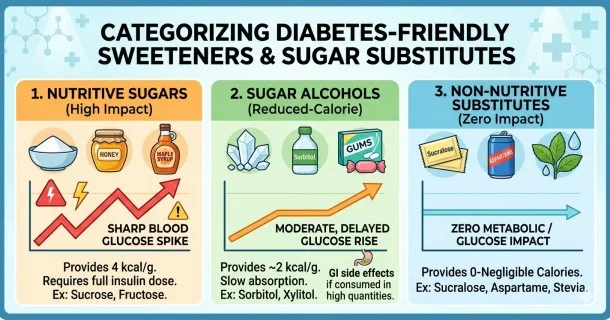
Managing Type 1 Diabetes (T1D) does not mean you have to completely eliminate sweet flavors from your lifestyle. However, navigating the wide world of sugar substitutes requires a clear understanding of biochemistry. Sweeteners are broadly split into three distinct categories: nutritive sweeteners (sugars), reduced-calorie sweeteners (sugar alcohols), and non-nutritive low-calorie sweeteners (artificial sugar substitutes). Learning how these compounds interact with your metabolism allows you to satisfy sweet cravings without causing unpredictable blood glucose fluctuations or miscalculating your mealtimes insulin bolus.
1. Classifying the Three Primary Types of Sweeteners
To effectively manage blood sugar levels, it is vital to know how different sweeteners behave once they enter your digestive tract:
A. Nutritive Sugars (High Glycemic Impact)
These are naturally occurring carbohydrates providing 4 calories per gram. They rapidly break down into glucose, flooding the bloodstream and demanding immediate exogenous insulin coverage. Examples include white sucrose (table sugar), brown sugar, cane sugar, raw turbinado, honey, maple syrup, and molasses.
B. Reduced-Calorie Sweeteners / Sugar Alcohols (Moderate Glycemic Impact)
Sugar alcohols are structural hybrids of sugar and alcohol molecules. They provide roughly 2 to 2.5 calories per gram—about half the energy load of standard sugars. Because they are absorbed slowly and incompletely in the small intestine, they cause a significantly smaller, delayed rise in blood glucose.
- Common Variants: Isomalt, maltitol, mannitol, sorbitol, and xylitol.
- The Gastrointestinal Trade-off: Because sugar alcohols travel mostly undigested into the large intestine, consuming them in high quantities can cause a strong osmotic effect, leading to bloating, gas, abdominal cramping, and diarrhea.
C. Non-Nutritive Low-Calorie Sweeteners (Negligible Glycemic Impact)
These are intensely concentrated sugar substitutes synthesized chemically or extracted from natural plants. Because they are not metabolized into glucose, they provide zero or negligible calories and do not raise blood sugar levels.
2. FDA-Approved Low-Calorie Sweeteners for Diabetes Control
The U.S. Food and Drug Administration (FDA) and the American Diabetes Association (ADA) recognize several high-intensity non-nutritive sweeteners as clinically safe for individuals with diabetes, each possessing unique functional properties:
- Sucralose: Highly stable under intense heat, making it an excellent choice for baking and cooking. It is widely used in commercial sugar-free processed foods.
- Acesulfame Potassium (Acesulfame-K): An heat-stable sweetener often blended with other substitutes to mask bitter aftertastes. It retains its sweet profile perfectly during high-temperature cooking.
- Aspartame: Exceptionally popular in cold foods and diet sodas, but breaks down and loses its sweetness when exposed to high temperatures. Clinical Warning: Individuals diagnosed with Phenylketonuria (PKU)—a rare genetic metabolic disorder—must strictly avoid aspartame, as their bodies cannot process its phenylalanine component.
- Saccharin: One of the oldest artificial sweeteners, suitable for both hot and cold liquids. Clinical Precaution: It is generally recommended to limit or avoid saccharin intake during pregnancy or breastfeeding, as it can cross the placental barrier.
- Stevia and Monk Fruit Extracts: Naturally derived, high-intensity non-nutritive sweeteners that deliver zero-glycemic sweetness without synthetic chemical processing.
3. Deciphering Deceptive Food Packaging Labels
Food manufacturers frequently utilize confusing label terminology that can mislead consumers trying to calculate carbohydrate intake. Always verify the Nutrition Facts panel and ingredients list rather than relying on front-of-package marketing:
- "Sugar-Free": The product contains fewer than 0.5 grams of natural sugar per serving. However, it may still contain significant amounts of starches, grain flours, or sugar alcohols that will raise your blood sugar.
- "No Sugar Added": No extra sucrose or corn syrup was added during industrial manufacturing. However, the raw food items used may be naturally rich in simple sugars—such as the fructose found in fruit juices or the lactose found in milk.
- "Reduced Sugar": The product contains at least 25% less sugar per serving compared to the standard, regular version of the same product. The overall carbohydrate load remains high.
- "All-Natural": The product is free from synthetic ingredients or artificial chemicals. This means it is sweetened with natural sugars like honey, agave, or real fruit juice, which will cause sharp hyperglycemic spikes.
4. Managing Intense Sweet Cravings Strategically
Attempting to eliminate sweet flavors entirely often backfires, triggering psychological fatigue and intense cravings. Instead, deploy these clinical strategies to maintain metabolic control:
The Carbohydrate Substitution Method
You can safely enjoy a traditional sugar-sweetened treat occasionally by using exact substitution. Determine the total carbohydrate count of the sweet item, and remove an equivalent amount of carbohydrates from your core meal (such as swapping out bread or rice for non-starchy vegetables). This keeps your total carbohydrate load identical, allowing you to cover the treat safely with your established insulin-to-carbohydrate ratio.
Calibrating Your Satiety Cues
Intense cravings for sweets can often be managed behaviorally. Introducing low-glycemic, savory elements—such as a small portion of fermented pickles—can shift taste receptor activation and effectively curb immediate sweet cravings. Prioritizing healthy fats and lean proteins during your main meals promotes prolonged satiety, reducing the physiological urge to snack on simple starches.
5. Summary Comparison of Major Sweetener Categories
| Sweetener Category | Caloric Content | Glycemic Impact | Common Examples | Insulin Requirement |
|---|---|---|---|---|
| Nutritive Sugars | High (4 kcal/g) | Rapid, Steep Spikes | Sucrose, Honey, Fructose | Full Bolus Dose Required |
| Sugar Alcohols | Moderate (2-2.5 kcal/g) | Slow, Delayed Rise | Sorbitol, Xylitol, Maltitol | Partial Bolus May Be Needed |
| Non-Nutritive Substitutes | Zero / Negligible | None | Sucralose, Aspartame, Stevia | Zero Insulin Coverage |
Frequently Asked Questions (FAQs)
Do I need to inject insulin for foods containing sugar alcohols like sorbitol or malititol?
Sugar alcohols do possess a moderate glycemic index, meaning they cause a slow, partial rise in blood glucose. A standard clinical calculation for larger portions is to subtract half (50%) of the sugar alcohol grams from the Total Carbohydrates on the label, and then dose your fast-acting insulin bolus for the remaining net carbohydrate value.
Why does a food labeled "Sugar-Free" still cause my blood glucose to spike?
"Sugar-Free" simply means a food contains less than 0.5 grams of pure sugar per serving. However, the product may be loaded with other complex carbohydrates, such as refined wheat flour, cornstarch, or maltodextrin. These starches break down directly into glucose during digestion, causing significant blood sugar spikes despite the "Sugar-Free" label.
Is sucralose or aspartame safe to use in hot beverages and home baking?
Sucralose is heat-stable and retains its chemical structure under high temperatures, making it fully safe and effective for baking and hot drinks. Aspartame, however, is heat-sensitive; it breaks down when exposed to high temperatures, losing its sweet flavor entirely. Aspartame should only be used in cold foods or added to hot liquids immediately before consumption.
How can I safely incorporate a small slice of real sugar-sweetened cake into my diet?
You can incorporate a small treat by utilizing the carbohydrate substitution method. First, identify the total grams of carbohydrates in the cake. Next, remove that exact amount of carbohydrates from your scheduled meal—such as skipping the rice or potato portion. Finally, administer your mealtimes rapid-acting insulin bolus based on your standard insulin-to-carbohydrate ratio to cover the substituted carbohydrate load.