Learn the official ADA screening criteria for type 2 diabetes. Compare FPG, OGTT, and HbA1c diagnostic ranges to catch insulin resistance early.
Type 2 Diabetes Screening and Diagnosis: Clinical Guidelines and Laboratory Metrics
Because type 2 diabetes can develop silently over several years, waiting for symptoms to appear before seeking a evaluation can allow microvascular complications to take root. Understanding who qualifies for screening and how diagnostic blood tests are interpreted helps individuals take control of their metabolic health.
Official ADA Screening Criteria: Who Should Be Tested?
The American Diabetes Association (ADA) outlines clear guidelines to identify individuals who require clinical screening, even if they show no symptoms of high blood sugar.
1. Age-Based Universal Screening
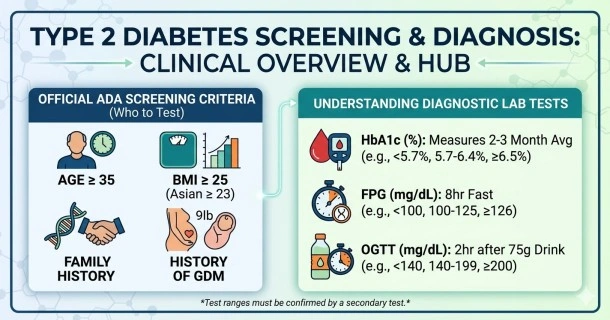
Universal screening for type 2 diabetes and prediabetes should begin for all asymptomatic adults at age 35. If the initial blood test results return normal, screening must be repeated at a minimum of every 3 years.
2. Risk Factor-Based Screening (Any Age)
Asymptomatic adults of any age who are overweight or obese—defined as a BMI ≥ 25 kg/m², or BMI ≥ 23 kg/m² for individuals of Asian ancestry—should undergo clinical screening if they possess one or more of the following additional risk factors:
- A first-degree relative (parent or sibling) diagnosed with type 2 diabetes.
- A documented history of prediabetes (an HbA1c between 5.7% and 6.4%, or prior impaired glucose tolerance).
- A history of gestational diabetes mellitus (GDM).
- Hypertension (blood pressure readings ≥ 130/80 mmHg or currently undergoing therapy for high blood pressure).
- Dyslipidemia (HDL cholesterol levels < 35 mg/dL and/or triglyceride levels > 250 mg/dL).
- A diagnosis of Polycystic Ovary Syndrome (PCOS) or clinical signs of severe insulin resistance (such as acanthosis nigricans).
- A history of cardiovascular disease or a highly sedentary lifestyle.
Understanding the Four Diagnostic Blood Tests
Endocrinologists utilize four distinct lab tests to screen for and confirm a diagnosis of type 2 diabetes. Except in cases of unequivocal severe hyperglycemia accompanied by acute symptoms, a positive result must be confirmed by a second test performed on a separate day or using a separate blood sample to rule out lab error.
| Diagnostic Blood Test | Normal Healthy Range | Prediabetes (Borderline) Range | Diabetes Range |
| Fasting Plasma Glucose (FPG) (Requires an 8-hour fast) | Less than 100 mg/dL | 100 to 125 mg/dL (Impaired Fasting Glucose) | 126 mg/dL or higher |
| 2-Hour Oral Glucose Tolerance Test (OGTT) (Tested 2 hours after a 75g glucose drink) | Less than 140 mg/dL | 140 to 199 mg/dL (Impaired Glucose Tolerance) | 200 mg/dL or higher |
| Glycated Hemoglobin (HbA1c) (Measures a 2-to-3-month blood sugar average) | Less than 5.7% | 5.7% to 6.4% | 6.5% or higher |
| Random Plasma Glucose Test (Done at any time; no fasting required) | Varying baselines | N/A | 200 mg/dL or higher (With symptoms present) |
Missing the Diagnosis: Why the Type of Test Matters
A common issue in early diabetes management is the clinical reliance on Fasting Plasma Glucose (FPG) tests alone. Historical epidemiological data highlights a significant difference in sensitivity between Impaired Fasting Glucose (IFG) and Impaired Glucose Tolerance (IGT).
- The Clinical Blindspot: Screening individuals using only fasting blood sugar criteria fails to identify a substantial percentage of people who have normal fasting numbers but exhibit severe blood sugar spikes after meals.
- The Post-Meal Spike: An Oral Glucose Tolerance Test (OGTT) or an HbA1c test is significantly more sensitive at capturing isolated Impaired Glucose Tolerance.
- The Ideal Approach: To ensure early, accurate detection, clinicians frequently order a combination of an HbA1c test alongside either an FPG or OGTT. This comprehensive approach catches peripheral muscle insulin resistance before it advances to full pancreatic failure.
Frequently Asked Questions (FAQ)
Can a fasting blood sugar test miss a diabetes diagnosis?
Yes. Relying strictly on a Fasting Plasma Glucose (FPG) test can miss cases of isolated Impaired Glucose Tolerance (IGT). Many individuals maintain a normal fasting glucose level under 100 mg/dL, yet their blood sugar levels spike dangerously high after eating carbohydrates, which is only captured via an OGTT or an HbA1c test.
Why did my blood sugar test show diabetes once, but the repeat test came back normal?
Fluctuations between tests typically occur when your metabolism is transitioning through the early, unstable stages of prediabetes or early type 2 diabetes. Because blood glucose values have not stabilized at a permanently high level, slight differences in daily stress, recent carbohydrate intake, physical movement, or sleep can cause numbers to cross back and forth over the diagnostic threshold lines.
What should I do immediately if my screening tests confirm prediabetes?
A prediabetes diagnosis should be treated as an actionable warning sign. According to findings from the Diabetes Prevention Program (DPP), implementing immediate lifestyle modifications—such as achieving a sustainable 5% to 7% weight reduction, completing 150 minutes of moderate weekly exercise, and shifting toward whole, low-glycemic foods—can reduce your risk of progressing to full type 2 diabetes by 58%.