Understand what hyperglycemia (high blood sugar) is. Explore the physiological definitions of fasting versus postprandial elevations and its impact on the body.
Understanding Hyperglycemia: A Comprehensive Introduction
Hyperglycemia is the medical term for an abnormally high concentration of glucose circulating in the blood. Derived from the Greek words hyper (excessive), glyc (sweet), and emia (of the blood), this condition serves as the hallmark physiological characteristic of diabetes mellitus. It signifies a metabolic breakdown where the body either lacks sufficient insulin or cannot effectively utilize the insulin it produces.
While brief, minor elevations in blood sugar are a normal response to eating, persistent or severe hyperglycemia is a toxic state. Left uncorrected, chronic elevation damages vascular structures and nerve pathways throughout the body, while acute, critical spikes can lead to immediate, life-threatening metabolic crises.
Clinical Definitions & Blood Sugar Ranges
In medical practice, hyperglycemia is not defined by a single static number. Instead, it is classified based on when the measurement occurs relative to food intake:
1. Fasting Hyperglycemia
This refers to blood glucose elevations after a period of prolonged fasting (at least 8 hours without caloric intake).
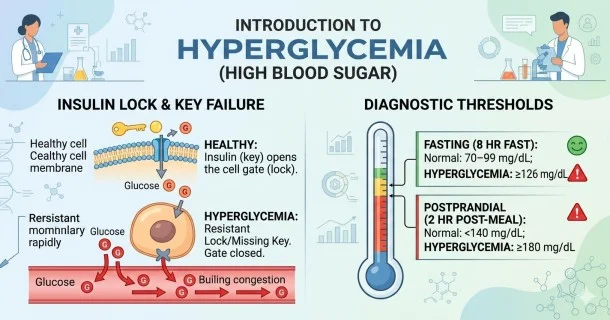
- Clinical Threshold: A fasting blood glucose measurement ≥126 mg/dL (7.0 mmol/L).
- Significance: Frequently points to insulin resistance in the liver, which causes the organ to inappropriately release stored glucose overnight.
2. Postprandial (Post-Meal) Hyperglycemia
This refers to high blood sugar levels measured after consuming a meal.
- Clinical Threshold: A blood glucose measurement ≥180 mg/dL (10.0 mmol/L) evaluated 1 to 2 hours after eating.
- Significance: Indicates that the body lacks the rapid-acting insulin phase necessary to safely process dietary carbohydrates.
| Metabolic State | Normal Range | Hyperglycemic Threshold |
|---|---|---|
| Fasting Blood Glucose | 70–99 mg/dL (3.9–5.5 mmol/L) | ≥126 mg/dL (7.0 mmol/L) |
| Postprandial (1-2 Hours Post-Meal) | <140 mg/dL (<7.8 mmol/L) | ≥180 mg/dL (10.0 mmol/L) |
How Hyperglycemia Develops: The Cellular Breakdown
To understand hyperglycemia, it is necessary to examine how glucose becomes trapped in the bloodstream at a cellular level:
[ Glucose Enters Blood Stream ]
│
┌─────────┴─────────┐
▼ ▼
[ Type 1 Diabetes ] [ Type 2 Diabetes ]
Insulin Producing Cells Are Resistant
Cells Destroyed To Insulin Keys
│ │
└─────────┬─────────┘
▼
[ Glucose Cannot Enter Cells ] ──► Accumulates in Blood ──► HYPERGLYCEMIA
- The Role of Insulin: Under healthy conditions, the pancreas secretes the hormone insulin when glucose enters the blood. Insulin acts like a key, binding to receptors on your muscle, fat, and liver cells to open the gates and let glucose leave the blood to be used for cellular energy.
- The Delivery Failure: In Type 1 diabetes, the pancreas suffers an autoimmune attack and completely stops manufacturing insulin; there are no keys available. In Type 2 diabetes, the body produces insulin, but the cell gates suffer from insulin resistance—the keys no longer fit the locks smoothly.
- The Blood Congestion: In both scenarios, the gates remain closed. Glucose is completely blocked from entering the cells, leaving it stuck inside the bloodstream. As you continue to consume food, the concentration of trapped sugar climbs, resulting in established clinical hyperglycemia.
Acute vs. Chronic Complications of Untreated High Blood Sugar
If high blood sugar levels are allowed to persist without medical management, the condition branches into two distinct categories of physiological danger:
- Acute Emergencies: A sudden, extreme spike in blood sugar can induce rapid metabolic crises. In Type 1 diabetes, a severe insulin deficit can trigger Diabetic Ketoacidosis (DKA). In Type 2 diabetes, extreme elevations can culminate in Hyperglycemic Hyperosmolar Syndrome (HHS), characterized by severe dehydration and altered consciousness.
- Chronic Vascular Complications: Over months and years, floating glucose molecules physically damage microvascular and macrovascular systems. This direct toxicity leads to long-term systemic damage, including diabetic nephropathy (kidney disease), retinopathy (eye damage), neuropathy (nerve damage), and significantly elevated risks for heart attacks and strokes.
To discover the progressive physical warning signs your body exhibits when blood sugar begins to rise, visit our guide on Recognizing Hyperglycemia Symptoms. If you want to explore the specific lifestyle habits or illnesses that structurally initiate these elevations, read our page on Hyperglycemia Causes & Triggers.
Frequently Asked Questions (FAQ)
At what exact number does high blood sugar become dangerous?
For routine management, a blood sugar reading consistently above 180 mg/dL is considered hyperglycemic and requires attention. However, acute danger typically escalates significantly when blood glucose exceeds 240 mg/dL to 250 mg/dL. At this clinical threshold, individuals—particularly those with Type 1 diabetes—must check their blood or urine for ketones to ensure they are not sliding into diabetic ketoacidosis.
Can a person have hyperglycemia without having diabetes?
Yes. Temporary or transient hyperglycemia can occur in individuals without diabetes during periods of extreme physiological stress. This is known as stress-induced hyperglycemia and is commonly triggered by major surgeries, severe physical trauma, a stroke, or a heart attack, where a massive surge of natural stress hormones overpowers normal insulin action. It can also occur as a direct side effect of certain medications, such as high-dose corticosteroids (like prednisone).
What is the difference between fasting and postprandial hyperglycemia?
The difference rests on when the blood test is taken. Fasting hyperglycemia is high blood sugar (126 mg/dL or higher) measured first thing in the morning after going without food for at least 8 hours. Postprandial hyperglycemia is high blood sugar (180 mg/dL or higher) measured 1 to 2 hours after you have eaten a meal, indicating your body cannot process the carbohydrates you consumed.
Why doesn't the body just flush out excess blood sugar naturally?
The body does attempt to eliminate excess sugar through the kidneys once blood glucose climbs above roughly 180 mg/dL—a threshold known as the renal threshold. However, the kidneys can only filter out a limited amount of sugar at a time. To flush it, they are forced to pull massive amounts of water out of your tissues, which rapidly leads to severe dehydration, compounding the metabolic danger rather than curing it.