Explore how Vitamin D and Calcium support pancreatic function and insulin sensitivity. Learn the scientific facts, daily dosages, and interactions.
Vitamin D and Calcium for Diabetes: Pancreatic Support and Insulin Sensitivity
Vitamin D and calcium function as an interconnected physiological duo essential for maintaining skeletal integrity and systemic metabolic balance. Beyond their foundational roles in bone health, emerging endocrinology research highlights a powerful relationship between optimization of these nutrients and the management of type 2 diabetes, prediabetes, and associated vascular complications.
Because clinical deficiencies in both Vitamin D and calcium remain highly widespread worldwide, addressing these dietary gaps offers a simple, low-cost strategy to support metabolic therapy.
The Metabolic Connection: Insulin and Glucose Regulation
In the context of metabolic syndrome and diabetes, Vitamin D and calcium operate via distinct cellular mechanisms to promote balanced glycemic control:
How Vitamin D Supports Glycemic Control
Vitamin D receptors (VDR) are present in various tissues throughout the body, including the insulin-producing beta cells of the pancreas and peripheral skeletal muscle tissue.
- Enhancing Insulin Secretion: Vitamin D stimulates pancreatic beta cells, directly promoting the healthy secretion of native insulin hormone.
- Improving Insulin Sensitivity: It modulates intracellular signaling pathways to optimize insulin sensitivity, helping fat and muscle tissues pull glucose out of the blood more efficiently.
- Reducing Metabolic Risk: Epidemiological trials confirm that low baseline serum levels of Vitamin D are strongly correlated with poor HbA1c control and an elevated risk of developing metabolic syndrome or type 2 diabetes.
The Essential Role of Calcium
Calcium ions act as crucial secondary chemical messengers within your body.
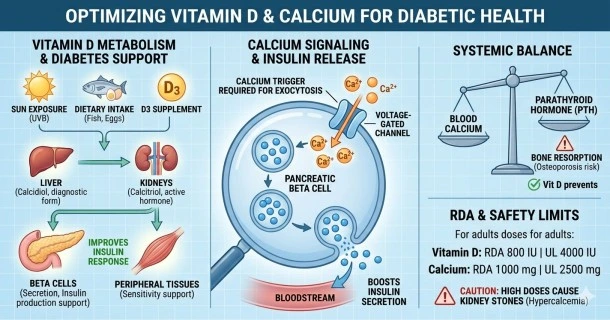
- Driving Exocytosis: A rapid influx of intracellular calcium is the exact chemical trigger required by pancreatic beta cells to release stored insulin into the bloodstream.
- Systemic Tissue Health: Adequate calcium levels are vital to maintain proper neuromuscular activity in the heart, coordinate skeletal muscle contractions, and support normal blood clotting mechanisms.
- The Depletion Cycle: If a severe Vitamin D deficiency blocks the gut from absorbing dietary calcium, the body is forced to release parathyroid hormone (PTH). This hormone strips calcium from your skeletal system, weakening bone mass and accelerating the risk of fractures and osteoporosis.
Biochemical Pathways: Reconstructing Vitamin D
To understand how supplementation works, it is important to observe how the body converts raw precursors into a biologically active hormone through distinct steps:
- Dermal Synthesis & Intake: Exposure to solar ultraviolet B (UVB) radiation triggers the creation of Vitamin D in skin cells, while dietary intake provides Vitamin D2 (ergocalciferol) or Vitamin D3 (cholecalciferol).
- Hepatic Hydroxylation: In the liver, enzymes convert these initial forms into 25-hydroxyvitamin D [25(OH)D], chemically termed calcidiol. This is the stable form measured by doctors in standard diagnostic blood tests.
- Renal Hydroxylation: In the kidneys, a secondary enzyme processes calcidiol into 1,25-dihydroxyvitamin D [1,25(OH)2D], known as calcitriol. Calcitriol is the fully activated, potent hormone responsible for coordinating intestinal calcium absorption and systemic tissue processes.
Recommended Dosages and Safety Parameters
Maintaining an optimal daily intake helps secure systemic benefits while keeping you safe from the hazards of over-supplementation.
Recommended Intake Levels
- Vitamin D RDA: The standard Recommended Dietary Allowance for adult men and women is 800 IU (20 mcg) per day. The strict Tolerable Upper Intake Level (UL) is 4000 IU (100 mcg) per day.
- Calcium RDA: The baseline recommendation for standard adults is 1,000 mg per day. The Tolerable Upper Intake Level (UL) is set at 2,500 mg per day.
Toxicity Vulnerabilities (Hypervitaminosis D)
Excessive, unmonitored intake of high-dose Vitamin D supplements can induce hypervitaminosis D. This toxicity causes hypercalcemia (abnormally high blood calcium levels), which presents clinically as:
- Persistent nausea, cyclic vomiting, and sharp loss of appetite.
- Cognitive confusion, fatigue, and severe cardiac arrhythmias.
- Painful kidney stones caused by excess mineral precipitation in the renal tract.
Similarly, over-consuming calcium via concentrated supplements (rather than food) can trigger chronic constipation and severely impede your gut's ability to absorb vital micro-minerals like iron and zinc.
Critical Medication Interactions
- Corticosteroids: Chronic prescription steroid use accelerates Vitamin D depletion and lowers intestinal calcium absorption mechanisms.
- Weight Loss and Cholesterol Meds: Drugs like Orlistat or Cholestyramine can lower the absorption of fat-soluble vitamins, including Vitamin D.
- Anticonvulsants: Medications such as phenobarbital and phenytoin induce hepatic enzymes that accelerate the breakdown and clearance of active Vitamin D from your body.
Dietary Sources and Choosing the Right Supplement Form
Prioritizing whole-food nutrient matrices alongside safe solar exposure forms the baseline of metabolic care.
Natural Food Sources
- Vitamin D Dense Options: Cod liver oil, wild-caught salmon, Atlantic tuna, fortified dairy milks, yogurts, and egg yolks.
- Calcium Dense Options: High-quality cheeses, raw almonds, broccoli, kale, sardines (with soft bones intact), tofu, and fresh turnip greens.
Selecting Supplement Compounds
- Vitamin D: Choose Vitamin D3 (cholecalciferol) over Vitamin D2. Clinical data proves that D3 is significantly more efficient at raising long-term circulating systemic calcidiol levels in human tissue.
- Calcium: Look for calcium citrate if you take medications or have sensitive digestion, as it absorbs well on an empty stomach. Calcium carbonate is cheaper and highly concentrated but requires food-triggered stomach acid for proper breakdown. To maximize your body's fractional absorption efficiency, divide your supplement intake into smaller doses of 500 mg or less taken throughout the day.
Frequently Asked Questions (FAQ)
Does Vitamin D help lower blood sugar in type 2 diabetes?
Vitamin D works gradually over time by interacting with specific cellular receptors on pancreatic beta cells and peripheral tissues. Clinical trials indicate that optimizing Vitamin D levels can help improve overall insulin sensitivity and enhance native insulin secretion, supporting blood sugar control in individuals who have a verified baseline deficiency.
Which form of Vitamin D is best for individuals with diabetes?
Vitamin D3 (cholecalciferol) is the preferred supplemental form for diabetic care. Clinical research establishes that Vitamin D3 is significantly more bioavailable and effective at raising and sustaining total circulating calcidiol concentrations in the blood compared to Vitamin D2 (ergocalciferol).
Why should I split my calcium supplement into doses under 500 mg?
The human intestinal tract faces a hard physiological limit when absorbing calcium. When you ingest more than 500 mg of elemental calcium at one time, the percentage of fractional absorption drops sharply. Splitting your intake into smaller doses taken several times a day ensures maximum absorption efficiency.