Learn when to intensify type 2 diabetes treatment with a basal-bolus insulin regimen, how to titrate doses safely, and how it compares to premixed insulin options.
Basal-Bolus Insulin Therapy for Type 2 Diabetes
Type 2 diabetes is a progressive condition characterized by a gradual decline in pancreatic beta-cell function over time. While many individuals manage their blood glucose initially with lifestyle modifications and oral medications, a substantial number will eventually require insulin therapy to maintain safe glycemic control.
When a maximum dose of non-insulin therapies no longer keeps blood glucose within target ranges, the typical next step is introducing a once-daily long-acting basal insulin. However, if target hemoglobin A1C goals are still not achieved, a more comprehensive approach—such as a basal-bolus insulin regimen—becomes necessary.
Understanding the Basal-Bolus Approach
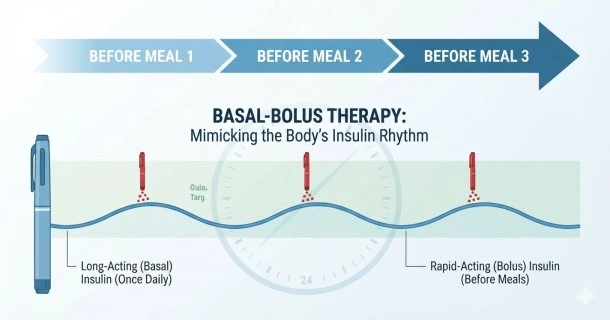
A basal-bolus insulin regimen is designed to closely mimic the body's natural insulin secretion. It combines two distinct types of insulin:
- Basal Insulin: Long-acting or ultra-long-acting insulin (such as glargine, detemir, or degludec) taken once or twice daily to provide a steady background level of insulin, keeping fasting blood glucose stable throughout the day and night.
- Bolus Insulin: Rapid-acting or short-acting insulin (such as lispro, aspart, glulisine, or regular human insulin) taken immediately before meals to manage postprandial (after-meal) blood glucose spikes.
For individuals who experience severe nighttime or fasting hyperglycemia, or those whose schedules require a lower-cost option, intermediate-acting insulins like NPH (Humulin N, Novolin N) administered at bedtime or twice daily may serve as an alternative. Clinical data shows that analog insulins (glargine and detemir) are associated with up to a 50% lower risk of nocturnal hypoglycemia and less weight gain compared to intermediate-acting NPH insulin.
When Should Insulin Therapy Be Intensified?
Intensification to a basal-bolus regimen is typically considered under specific clinical circumstances:
- Elevated A1C Despite Target Fasting Glucose: If your morning fasting blood glucose readings are consistently within your target range, but your overall A1C remains above your individualized goal (typically 7% for many adults), it suggests that significant blood sugar spikes are occurring after meals.
- Basal Insulin Dose Limitations: Further increasing the basal insulin dose may be counterproductive or unsafe if it triggers episodes of hypoglycemia (low blood sugar), particularly overnight or between meals.
- Severe Insulin Deficiency: Advanced progression of type 2 diabetes where the body can no longer produce sufficient mealtime insulin.
General Principles of Insulin Dosing and Dosing Adjustments
Insulin requirements vary heavily based on individual metabolic needs, body weight, renal function, and lifestyle factors. Clinicians typically initiate and adjust therapy using generalized, label-based guidelines:
- Initiation: For individuals experiencing mild metabolic stress or those at an elevated risk for low blood sugar (such as elderly patients or those with chronic kidney or liver disease), clinicians frequently initiate conservative weight-based dosing, often starting around 0.2 units/kg per day. For others without these complications, a standard starting range of 0.3 to 0.5 units/kg per day is common.
- Distribution: A classic basal-bolus approach frequently splits the total daily insulin requirement evenly, allocating 50% to the basal insulin and dividing the remaining 50% among the day's primary meals as bolus injections.
- Mealtime Adjustments: Bolus doses are often initiated conservatively at 4 to 6 units per meal. The dose is then tailored based on pre-meal glucose tracking or calculated using an insulin-to-carbohydrate ratio (similar to type 1 diabetes management) to match the carbohydrate content of the upcoming meal. Doses may need downward adjustment if physical activity is anticipated within 2 to 3 hours after eating.
- Safe Dosing Adjustments: Under medical supervision, doses are typically titrated by adding 2 units every 4 to 7 days until target glucose ranges are achieved, provided hypoglycemia does not occur.
Alternative Approaches: Premixed Insulin Regimens
For individuals who find a multi-injection basal-bolus regimen (which often requires 4 or more injections per day) challenging to manage, a simplified premixed insulin regimen may be considered.
Premixed insulins combine a fixed ratio of intermediate-acting or long-acting protaminated insulin with a rapid-acting or short-acting insulin in a single vial or pen (such as biphasic insulin aspart or lispro mix). Administered two to three times daily before meals, these regimens offer a less complex schedule.
However, fixed-ratio premixed insulins provide less flexibility for variable meal times or varying carbohydrate counts. Because of this rigidity, guidelines often suggest a slightly more relaxed glycemic target (such as an A1C goal of less than 7.5%) for individuals utilizing premixed options, compared to the strict sub-7% goals achievable with highly customizable basal-bolus regimens. Both approaches demonstrate comparable rates of overall hypoglycemia when properly managed.
Frequently Asked Questions (FAQs)
What is the difference between basal and bolus insulin?
Basal insulin is a long-acting insulin that provides a steady background level of insulin to control blood sugar between meals and overnight. Bolus insulin is a rapid- or short-acting insulin taken right before meals to control the sharp rise in blood sugar that occurs after eating.
When does a person with type 2 diabetes need to add mealtime insulin?
Mealtime (bolus) insulin is typically added when a person's fasting morning blood sugars are at their target level, but their overall A1C remains high. This indicates that blood sugar spikes after meals are keeping the average too high, and further increasing long-acting basal insulin would risk causing hypoglycemia.
How is a basal-bolus insulin dose calculated?
A typical clinical starting point is to calculate a total daily insulin dose based on weight (often 0.3 to 0.5 units per kilogram). This total is frequently split 50/50, where half is given as the daily basal injection and the other half is divided evenly among the primary meals as bolus injections. All doses must be verified and adjusted by a healthcare professional.
Is premixed insulin better than a basal-bolus regimen?
Neither is universally "better," as the choice depends on lifestyle and medical needs. A basal-bolus regimen requires more daily injections (usually 4 or more) but offers excellent flexibility and precise control. Premixed insulin reduces the number of injections (usually 2 to 3) but requires highly consistent meal sizes and schedules.