Learn when to start insulin therapy for type 2 diabetes. Explore basal vs. bolus regimens, painless injection needles, and side effect prevention tips.
Type 2 Diabetes Insulin Therapy: Guide to Regimens, Timing, and Safe Dosing
Type 2 diabetes insulin therapy becomes a necessary step for many individuals due to the progressive decline in insulin production by pancreatic beta cells. While shifting from oral pills to injectables often causes anxiety, introducing insulin is a powerful way to take control of your metabolic health, clear away persistent fatigue, and prevent long-term diabetes complications.
Understanding when to start insulin, how modern painless needles work, and how to safely navigate the transition can help you build an effective daily management routine.
When is It Time to Start Insulin Therapy?
At the early stages, type 2 diabetes is typically managed with lifestyle changes and oral medications or GLP-1 receptor agonists. However, as the condition evolves, your healthcare provider may introduce insulin.
Key Clinical Triggers for Insulin Initiation
- Maxed-Out Oral Options: If a "triple-therapy" drug regimen (taking maximum doses of three distinct classes of diabetes pills) fails to achieve an A1C under 7.0% or keep your fasting blood sugar below 130 mg/dL, insulin is added to provide direct glycemic support.
- Severe Hyperglycemia Spikes: If your fasting blood glucose spikes over 250 mg/dL (13.89 mmol/L) or your HbA1C is extremely high, your doctor may prescribe insulin immediately to relieve the severe stress on your pancreas (known as glucose toxicity). Once your levels stabilize, it is sometimes possible to transition back to oral therapies.
- Organ Health Considerations: For elderly individuals or those managing pre-existing heart disease or moderate-to-severe kidney failure, insulin is often chosen by clinicians as the safest, most reliable tool because it bypasses hepatic and renal breakdown pathways required by many pills.
- Temporary Clinical Windows: You may require temporary insulin therapy during acute illnesses, major infections, or surrounding surgical procedures when physical stress causes blood sugar to rise and renders standard pills ineffective.
- Long-Term Disease Progression: Statistically, about one in three individuals with type 2 diabetes will require insulin therapy after living with the condition for 10 to 15 years.
Overcoming the Fear of Needles: The Modern Reality
A highly common barrier to starting treatment is the fear of injections. However, modern medical technology has made standard insulin delivery virtually painless.
- Ultra-Thin Gauges: Modern insulin pens and syringes utilize micro-fine needles that are typically 30 or 31 gauge. These needles are significantly thinner than the lancets used for finger-prick blood glucose testing.
- Short Lengths: Standard needles are incredibly short—often just 5/16 inch (8mm) or 5/32 inch (4mm). They are designed to deliver insulin perfectly into the subcutaneous fat layer right under your skin, completely avoiding the underlying muscle tissue.
- The Comfort Factor: Subcutaneous injections are so faint that many patients have to visually inspect the injection site to confirm that the skin was pierced and the insulin was successfully delivered.
Common Insulin Regimens for Type 2 Diabetes
Your endocrinologist will customize an insulin routine based on your daily lifestyle, age, and blood sugar patterns.
1. Basal Insulin Therapy (The Standard Starting Point)
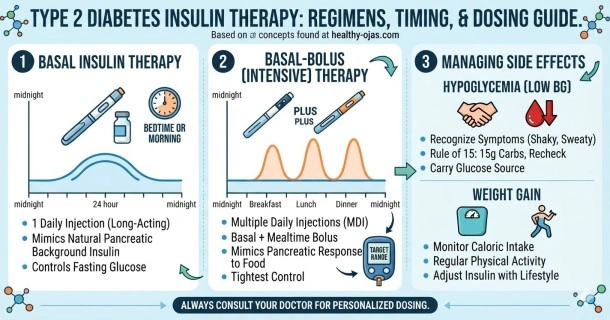
The most common way to start is by adding a single daily dose of basal insulin while keeping your baseline metformin prescription active. Basal insulin provides a steady, low level of insulin throughout the day and night to keep your blood sugar flat when you aren't eating.
- NPH Insulin: An intermediate-acting insulin that is cost-effective and highly reliable. It is typically injected in the evening.
- Long-Acting Insulin Analogs: Medications like glargine (Lantus) or detemir (Levemir) provide a steady 24-hour release. Their main clinical advantage over NPH is a significant reduction in nighttime (nocturnal) hypoglycemia.
- Target Goal: The primary aim of basal insulin is to keep your fasting plasma glucose at or below 100 mg/dL (5.6 mmol/L).
2. Basal-Bolus Insulin Therapy (Intensive Control)
If your fasting blood sugar is stable but your numbers experience dangerous spikes right after eating, your doctor may advance your treatment to a basal-bolus regimen. This introduces a rapid-acting (bolus) insulin injection immediately before your major meals to handle carbohydrate intake.
Managing Side Effects: Hypoglycemia and Weight Gain
While insulin is exceptionally effective at lowering glucose, intensive therapy introduces two primary side effects that require careful tracking:
- Hypoglycemia (Low Blood Sugar): The most significant limiting factor in tight blood sugar management. While type 2 diabetes offers some natural protection against severe crashes due to insulin resistance, drops can still happen.
- Weight Gain: Patients often notice a 2 to 4 kg (4.4 to 8.8 lbs) weight increase when starting insulin. This happens because your body stops flushing excess sugar out through your urine and begins absorbing those calories properly into your cells for energy.
- Prevention Strategy: Maintaining a predictable, fiber-rich carbohydrate intake and timing your physical activity shortly after your insulin doses can minimize both weight gain and low blood sugar drops.
Frequently Asked Questions (FAQs)
Why do people with type 2 diabetes eventually need insulin?
Type 2 diabetes is a progressive condition. Over time, the insulin-producing beta cells in your pancreas can slowly wear out and produce less natural insulin. When lifestyle modifications and multiple oral medications can no longer keep your blood sugar stable, insulin injections step in to provide the exact amount your body is missing.
When is insulin considered the safest treatment for type 2 diabetes?
Insulin is widely considered the safest and most reliable treatment option for elderly individuals, people with significant heart disease, or patients suffering from moderate-to-severe kidney impairment. This is because insulin acts directly on your cells and does not place metabolic strain on your liver or kidneys like many oral medications do.
What is the difference between basal and bolus insulin?
Basal insulin is an intermediate or long-acting insulin taken once a day (usually at bedtime) to keep your blood sugar steady overnight and between meals. Bolus insulin is a rapid-acting insulin injected right before meals to quickly process carbohydrates and flatten post-meal blood sugar spikes.
Why does starting insulin cause weight gain, and how can I stop it?
Before starting insulin, high blood sugar often means your body is wasting calories by flushing unused glucose out through your urine. Once insulin therapy starts, your cells can finally absorb and store that glucose for energy, which can cause a 2 to 4 kg weight increase. You can prevent this by managing your daily carbohydrate portions and staying physically active.