How does gestational diabetes affect your baby? Learn about macrosomia, newborn low blood sugar risks, lung maturity, and essential third-trimester kick counts.
Gestational Diabetes Impact on Baby: Risks, Fetal Monitoring, and Neonatal Care
If you have been diagnosed with gestational diabetes mellitus (GDM), your primary concern is naturally your child's well-being. Because gestational diabetes typically develops in the second or third trimester—well after the baby's vital body organs and structures have formed—it does not cause structural congenital birth defects.
However, elevated maternal blood sugar alters the environment in the womb, which can introduce specific prenatal, labor, and long-term health risks for your child. Understanding these impacts enables your healthcare team to deploy highly effective tracking and immediate neonatal protocols to protect your newborn.
How Gestational Diabetes Affects Fetal Development
When maternal blood sugar is high, excess glucose continuously crosses the placenta. While maternal insulin cannot pass through the placental barrier, the fetus reacts to the heavy influx of sugar by producing extra insulin from its own pancreas.
This combination of abundant glucose and high fetal insulin can result in several clinical complications:
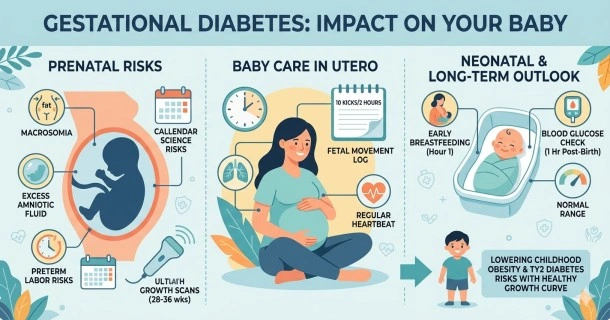
- Macrosomia (Excessive Growth): The fetus converts the unneeded extra energy into stored fat, leading to an unusually large baby. Macrosomia complicates labor, increasing the risk of the baby's shoulders becoming wedged in the birth canal (shoulder dystocia) or requiring surgical delivery.
- Neonatal Hypoglycemia (Low Blood Sugar): After delivery, the baby is instantly cut off from the mother's high-sugar blood supply, but their pancreas continues to produce large amounts of insulin. This can cause their blood sugar to crash shortly after birth.
- Infant Respiratory Distress Syndrome: High levels of insulin in the fetus can actively delay the maturation of the lungs, making it harder for some newborns to breathe independently right after birth.
- Hyperbilirubinemia (Jaundice): Babies exposed to high glucose levels in utero have a higher statistical incidence of neonatal jaundice, requiring phototherapy.
Essential Fetal Care Protocols During Pregnancy
To keep your baby healthy and plan a safe delivery, your medical team will utilize a series of targeted fetal assessments to track growth and amniotic fluid levels.
1. Advanced Ultrasound Scheduling
- Anatomical Survey (Weeks 18 to 20): If you are diagnosed early with GDM (before week 20), an early detailed scan evaluates structural development.
- Third-Trimester Growth Scans: You will undergo regular serial scans at weeks 28 to 30 and weeks 34 to 36. These ultrasounds track fetal biometry to watch for macrosomia and provide precise amniotic fluid estimations.
2. Daily Fetal Activity Tracking (Kick Counts)
Your provider will instruct you to track fetal movement daily, especially after meals. A standard tracking method involves lying comfortably on your side and measuring how long it takes to feel 10 distinct movements or kicks.
- The Safety Baseline: You should easily count at least 10 kicks within a 2-hour window.
- When to Call: If fetal movements drop below this baseline or change noticeably, contact your OB/GYN or labor unit immediately. Fetal heart health will also be verified via routine electronic auscultation at every prenatal checkup.
Immediate Postpartum Care for Your Newborn
Right after birth, specialized clinical guidelines are enacted to smoothly manage the baby's transition and prevent metabolic crashes.
- Early Breastfeeding Initiatives: Initiating breastfeeding within the first hour of life is the gold standard for preventing neonatal drops in sugar. If the infant cannot suck efficiently, expressed breast milk or specialized formula is given.
- Strict Blood Glucose Monitoring: Clinical guidelines require checking the newborn's blood sugar within 1 hour of delivery. A capillary reading below 44 mg/dL indicates neonatal low blood sugar. Tracking continues every 4 hours until the infant maintains four stable, normal readings.
- Mode of Delivery: While a GDM diagnosis increases the statistical likelihood of a Cesarean section—accounting for 50% to 60% of diabetic deliveries due to large fetal size—a safe vaginal delivery remains the primary goal for most obstetricians if blood sugar is well-controlled.
Long-Term Health Outlook and Gestational Programming
The impacts of gestational diabetes do not completely end at birth. The "Fetal Origin of Adult Disease" hypothesis indicates that stresses or high-glucose environments encountered by a fetus during sensitive periods can trigger permanent physiological changes. This process is known as gestational metabolic programming.
Children born to mothers with poorly managed gestational diabetes carry a higher statistical risk of developing childhood obesity, early metabolic syndrome, and type 2 diabetes as young adults.
The Protective Power of Breastfeeding
You can actively combat these long-term risks through nursing. Breastfeeding provides exceptional metabolic benefits for both you and your child. Studies show that infants who are breastfed and maintain a healthy childhood growth curve display a significantly lower lifetime risk of type 2 diabetes.
If breastfeeding is not a viable option for you, bottle-feeding safe alternatives while closely managing childhood nutrition provides excellent, healthy outcomes. Explore our next guide on [Preventing Diabetes After Pregnancy] to secure your family's metabolic health.
Frequently Asked Questions (FAQ)
Will my baby be born with diabetes if I have gestational diabetes?
No, your baby will not be born with diabetes. Gestational diabetes causes high blood sugar in the mother, not permanent diabetes in the infant. While your child does inherit your genetic background—giving them a slightly elevated lifetime predisposition—they will be born with standard blood sugar processing structures.
Why does gestational diabetes cause a baby to grow too large?
When your blood sugar is elevated, the extra glucose passes directly through the placenta to your baby. Because the baby receives far more energy than it requires to develop, its body stores this excess sugar directly as fat tissue, leading to a condition called macrosomia (a birth weight over 9 pounds or 4,000 grams).
What happens if a newborn's blood sugar drops too low after birth?
Mild post-birth low blood sugar is very common and easily treatable via immediate breastfeeding, expressed milk, or a temporary glucose solution. If the drop is severe or accompanied by signs like tremors or lethargy, neonatal teams may administer intravenous glucose to stabilize the baby's levels safely.