Understand Hyperglycemic Hyperosmolar Syndrome (HHS). Learn its clinical diagnostic criteria, physiological mechanism, and how it differs from DKA.
Understanding Hyperglycemic Hyperosmolar Syndrome (HHS)
Hyperglycemic Hyperosmolar Syndrome (HHS) is an acute, life-threatening metabolic complication of diabetes mellitus characterized by extreme blood sugar elevations and severe, systemic dehydration. While it can occur in anyone with diabetes, it is most frequently diagnosed in older adults managing Type 2 diabetes.
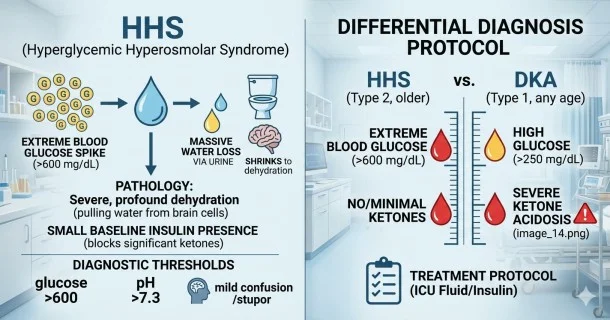
Unlike diabetic ketoacidosis (DKA), individuals experiencing HHS retain a small amount of baseline insulin production. This tiny amount of remaining insulin is just enough to block the body from rapidly breaking down fat into acidic ketones, meaning the blood does not become highly acidic. However, because there isn't enough insulin to actually lower blood glucose, sugar concentrations climb to extreme levels. This turns the blood highly concentrated (hyperosmolar), pulling massive amounts of water out of the body's vital organs and brain tissue. HHS carries a high mortality rate and requires immediate emergency medical treatment.
How HHS Develops: The Pathophysiology
To understand HHS, it helps to see what happens inside the body when extreme hyperglycemia triggers an osmotic crisis:
[ Relative Insulin Deficiency + Stressor ]
│
├─►Extreme Hyperglycemia (Sugar >600 mg/dL) ─►Blood turns highly concentrated
│
└─►Massive Osmotic Diuresis ─►Severe Fluid Loss ─►Profound Organ Dehydration
│
└─►Small Baseline Insulin Present ─►Blocks Lipolysis ─►No Significant Ketones (No DKA)
- Extreme Blood Sugar Spikes: Driven by an underlying illness, infection, or missed medication, stress hormones skyrocket and drive blood glucose to extreme heights.
- The Hyperosmolar Shift: As glucose concentrations soar, the blood becomes highly concentrated (hyperosmolar). This high osmotic pressure physically draws water out of the body’s cells and straight into the bloodstream.
- Massive Fluid Loss (Osmotic Diuresis): The kidneys attempt to filter out this extreme tidal wave of sugar. To do so, they flush out massive amounts of water, resulting in profound, life-threatening dehydration. The average individual experiencing HHS can lose up to 10 to 12 liters of total body fluid.
- Neurological Depression: As brain cells are systematically stripped of water to satisfy the high concentration of the blood, an individual develops advanced neurological complications, ranging from severe confusion to a complete diabetic coma.
Clinical Diagnostic Criteria for HHS
Medical professionals differentiate HHS from other diabetic emergencies using a specific set of laboratory markers:
| Diagnostic Metric | Clinical Threshold Value for HHS |
|---|---|
| Plasma Glucose (Blood Sugar) | Extremely elevated, typically ≥600 mg/dL (33.3 mmol/L). |
| Serum Osmolality (Concentration) | Highly elevated, >320 mOsm/kg (indicating extreme dehydration). |
| Arterial or Venous Blood pH | Normal to mildly altered, >7.3 (indicating no severe systemic acidification). |
| Serum Bicarbonate | Normal to minimal depletion, >15 mEq/L. |
| Serum & Urine Ketones | Absent, trace, or minimal. |
| Mental Status | Ranging from mild stupor and severe confusion to a complete coma. |
Direct Comparison: HHS vs. Diabetic Ketoacidosis (DKA)
Because both conditions represent severe high blood sugar crises, they are frequently confused. However, their underlying chemistry is entirely distinct:
| Clinical Feature | Hyperglycemic Hyperosmolar Syndrome (HHS) | Diabetic Ketoacidosis (DKA) |
|---|---|---|
| Primary Patient Population | Primarily Type 2 Diabetes (older adults). | Primarily Type 1 Diabetes (any age). |
| Typical Blood Sugar Level | Extreme: ≥600 mg/dL | High: ≥250 mg/dL. |
| Blood Acidity (pH) | Normal: >7.3 | Acidic: <7.3. |
| Ketone Production | Absent or Minimal. | Markedly Elevated. |
| Onset Timeline | Slow: Develops over days to weeks. | Rapid: Develops within 24 hours. |
To learn about the specific lifestyle choices or physical illnesses that structurally initiate this metabolic crisis, visit our page on Hyperglycemia Causes & Triggers. For a foundational look at how high blood sugar impacts your cells, read our Introduction to Hyperglycemia.
Frequently Asked Questions (FAQ)
What is the primary difference between HHS and DKA?
The primary difference is the presence of ketones and the severity of blood sugar elevation. In DKA, a total lack of insulin forces the body to burn fat, creating high levels of acidic ketones. In HHS, there is enough natural insulin to stop fat breakdown (so no significant ketones form), but not enough insulin to control blood sugar. As a result, blood sugar climbs much higher in HHS (often above 600 mg/dL) than in DKA, causing much more severe dehydration.
What are the main triggers that cause HHS to develop?
HHS is most commonly triggered by an acute underlying medical illness or systemic infection, such as pneumonia or a urinary tract infection (UTI). Other common triggers include severe cardiovascular events (like a heart attack or stroke), severe dehydration, or forgetting to take baseline diabetes medications and insulin therapies.
How fast does Hyperglycemic Hyperosmolar Syndrome develop?
Unlike DKA, which can manifest in less than 24 hours, HHS typically has a slow, insidious onset. It often develops gradually over several days or weeks. Because the early signs of high blood sugar are easy to ignore or mistake for aging, the condition frequently goes unnoticed until severe dehydration causes immediate neurological issues.
How is HHS treated in a hospital setting?
HHS treatment requires a highly specialized, cautious medical protocol focused on aggressive intravenous (IV) fluid resuscitation to correct the extreme dehydration. Doctors simultaneously administer a continuous insulin infusion to slowly lower blood sugar levels. Because dropping the blood's concentration too rapidly can cause dangerous fluid shifts in the brain (cerebral edema), medical teams track electrolytes and fluid balance every hour in an intensive care setting.