Discover how diabetic ketoacidosis (DKA) is treated. Learn about the medical protocols for fluid resuscitation, insulin therapy, and managing vital electrolytes.
Diabetic Ketoacidosis (DKA) Treatment Protocols & Medical Management
Diabetic ketoacidosis (DKA) is a severe medical crisis that requires immediate hospitalization, typically in an intensive care unit (ICU) or specialized high-dependency ward. Because it alters your blood chemistry, DKA cannot be treated safely at home. Medical management focuses on stabilizing your metabolism, neutralizing toxic acid buildup, and restoring safe fluid balance.
Clinical treatment requires careful, round-the-clock monitoring of your blood glucose, electrolyte concentrations, and fluid input/output. Doctors follow a highly structured, step-by-step protocol to resolve DKA safely.
The Three Core Pillars of Clinical DKA Treatment
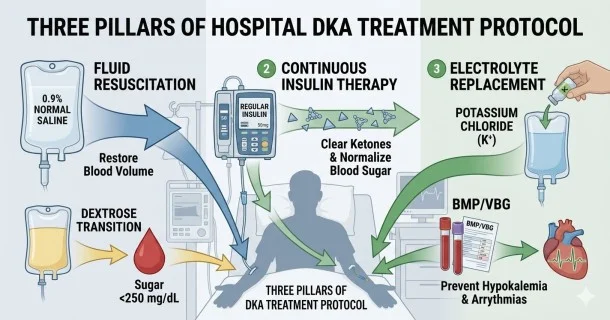
Hospital care for diabetic ketoacidosis rests on three essential therapies administered simultaneously:
1. Rapid Intravenous (IV) Fluid Resuscitation
Severe dehydration is a hallmark of DKA, with the average patient losing massive amounts of body water due to frequent urination. Fluid replacement is the absolute first step in treatment.
- Mechanism: Doctors administer large volumes of 0.9% normal saline through an intravenous line to rehydrate your tissues and restore stable blood pressure.
- Transition: Once your blood glucose drops to around 200–250 mg/dL, doctors shift the fluid to a dextrose-containing solution (like D5W with half-normal saline). This allows the continuous administration of insulin without dropping your blood sugar too low.
2. Continuous Intravenous Insulin Therapy
Insulin is the only mechanism that can stop the body from burning fat and producing dangerous ketones.
- Protocol: Patients receive a continuous infusion of Regular (Short-Acting) Insulin via an IV pump. This allows medical staff to fine-tune the dosage every hour based on real-time blood tests.
- Goal: The primary goal of insulin therapy is not just lowering blood sugar, but stopping lipolysis (fat breakdown) so your liver ceases ketone production. This allows your blood pH to return to normal.
3. Critical Electrolyte Replacement (Focus on Potassium)
Insulin forces potassium out of the bloodstream and directly into your cells. If your potassium levels drop too low (hypokalemia), it can cause fatal heart rhythm abnormalities (arrhythmias).
- Monitoring: Blood is drawn every 1–2 hours to measure potassium, sodium, and magnesium.
- Correction: Doctors add precise doses of potassium chloride directly into your IV bags. If a patient's baseline potassium is critically low upon arrival, insulin therapy is temporarily delayed until potassium levels are safely brought back up.
The Three Stages of Hospital Recovery
| Phase | Medical Action | Clinical Target |
|---|---|---|
| Phase 1: Stabilization | Aggressive IV fluids and continuous insulin infusion. | Restore blood pressure, clear ketones, and begin lowering blood glucose. |
| Phase 2: Correction | Introduce dextrose fluids into the IV line; replace missing potassium. | Close the anion gap, bring blood pH back above 7.3, and raise bicarbonate to >18 mEq/L. |
| Phase 3: Transition | Discontinue the IV pump and administer the first subcutaneous insulin injection. | Safely transition back to routine home diabetes management after eating food normally. |
Potential Risks and Complications of DKA Treatment
While the DKA protocol is highly effective, changing your body's chemistry too rapidly carries built-in medical risks that physicians must actively prevent:
- Cerebral Edema (Brain Swelling): If blood glucose or fluid levels drop too rapidly—particularly in children—water can rush into brain tissue, causing severe swelling. This is a critical risk that requires a gradual, measured treatment pace.
- Hypokalemia (Low Potassium): Driven by insulin pushing potassium into cells, this requires constant vigilance to protect heart function.
- Hypoglycemia (Low Blood Sugar): Prevented by carefully introducing dextrose into the IV fluids well before sugar levels plummet to dangerous thresholds.
To understand the physical warning signs that mandate immediate hospitalization, read our guide on Recognizing Diabetic Ketoacidosis Symptoms. To review how to test for ketones at home during a sick day, explore our page on How to Test for Diabetic Ketoacidosis.
Frequently Asked Questions (FAQ)
How long does it take to recover from diabetic ketoacidosis in the hospital?
Most uncomplicated episodes of DKA resolve within 12 to 24 hours of starting the clinical protocol. However, complete hospitalization may extend across several days depending on the severity of the initial acidosis, how long it takes the patient to eat solid food safely, and the treatment required for the underlying trigger (like a severe infection).
Why do doctors give sugar (dextrose) fluids during DKA treatment?
It sounds counterintuitive, but adding sugar to the IV is a vital safety measure. Once blood glucose drops below 250 mg/dL, insulin is still required to completely turn off ketone production. Adding dextrose to the IV prevents the patient from developing severe low blood sugar (hypoglycemia) while allowing the insulin pump to continue clearing the remaining blood acids safely.
Can diabetic ketoacidosis be treated at home?
No, DKA cannot be treated at home. It requires precise, hourly adjustments of intravenous insulin, massive fluid volumes, and constant electrolyte replacement that can only be measured via frequent hospital laboratory blood draws. Attempting to treat established ketoacidosis at home can lead to fatal electrolyte imbalances or severe organ damage.
When is a patient considered fully recovered from DKA?
A patient is clinically considered to have resolved their DKA when their blood pH climbs above 7.3, their serum bicarbonate rises above 18 mEq/L, the calculated anion gap closes, and they are mentally alert and able to eat and retain regular meals without vomiting.