Understand what diabetic ketoacidosis (DKA) is, how it develops at a cellular level, clinical diagnostic criteria, and how it differs from safe dietary ketosis.
Understanding Diabetic Ketoacidosis (DKA): An Introduction
Diabetic ketoacidosis (DKA) is an acute, life-threatening metabolic complication of diabetes mellitus characterized by a critical shortage of circulating insulin. While it most frequently affects individuals with Type 1 diabetes, it can also occur in individuals with Type 2 diabetes under extreme physiological stress or when using certain medications.
When the body lacks the insulin needed to move sugar from the bloodstream into the cells, it undergoes cellular starvation. To survive, the body rapidly shifts its metabolism to burn fat for fuel, generating high levels of organic blood acids called ketone bodies. Left untreated, the accumulation of these ketones drops the blood’s pH to dangerous levels, leading to a state called metabolic acidosis. DKA is a medical emergency that requires immediate hospitalization and specialized critical care.
How Diabetic Ketoacidosis Develops: The Pathophysiology
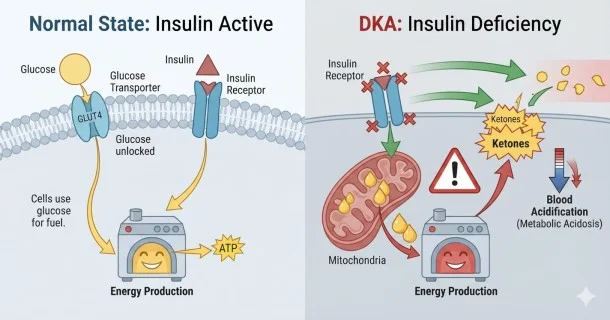
To understand DKA, it helps to see what happens inside the body when insulin levels drop critically low:
[Critical Insulin Deficiency]
│
├─►Cells Starve (Cannot absorb glucose) ─► Liver releases more glucose ─► Hyperglycemia & Dehydration
│
└─►Unrestrained Lipolysis (Fat breakdown) ─► Liver creates excess Ketones ─► Metabolic Acidosis
- Cellular Starvation & Hormone Surge: Without insulin, your cells cannot absorb glucose from the blood. Believing it is starving, the body releases counter-regulatory "stress" hormones like glucagon, epinephrine, cortisol, and growth hormone.
- Flooding the Blood with Sugar: These stress hormones prompt the liver to aggressively break down glycogen stores and produce new glucose. Because there is still no insulin to help cells use this sugar, blood glucose climbs to extreme levels (hyperglycemia).
- Rapid Fat Breakdown (Lipolysis): Simultaneously, the lack of insulin allows fat tissue to break down rapidly into free fatty acids. These fatty acids travel to the liver, where they are converted into acidic ketone bodies: acetoacetate and β-hydroxybutyrate.
- Blood Acidification & Osmotic Diuresis: As ketones overwhelm the bloodstream, they consume the body's natural bicarbonate buffers, dropping the blood pH below normal limits. Meanwhile, the kidneys attempt to flush out the excess glucose and ketones through the urine, pulling massive amounts of water and vital electrolytes (like potassium and sodium) out with them, causing severe, life-threatening dehydration.
Clinical Diagnostic Criteria for DKA
Medical professionals diagnose diabetic ketoacidosis based on a specific "triad" of clinical findings:
| Diagnostic Metric | Clinical Threshold Value |
|---|---|
| Blood Glucose | Typically ≥200 mg/dL to 250 mg/dL (though "euglycemic DKA" can present with normal sugar levels). |
| Blood pH (Acid-Base Balance) | Arterial or venous pH < 7.3. Normal blood pH is roughly 7.35 to 7.45. |
| Serum Bicarbonate | ≤18 mEq/L (indicating that the body's acid buffers are being severely depleted). |
| Ketones | Markedly elevated concentrations of ketones in the blood (≥3.0 mmol/L) or high levels in the urine. |
Nutritional Ketosis vs. Diabetic Ketoacidosis (DKA)
A common point of confusion among web searchers is the difference between safe ketosis (induced by fasting or a low-carb ketogenic diet) and diabetic ketoacidosis. They are fundamentally different biological states:
- Nutritional Ketosis: This is a controlled, safe physiological state. Because insulin production remains functional, the body tightly regulates ketone production, capping blood ketone concentrations safely between 0.5 to 3.0 mmol/L. Blood pH remains completely normal.
- Diabetic Ketoacidosis (DKA): This is an uncontrolled, life-threatening metabolic crisis. Due to an absolute or near-absolute lack of insulin signaling, ketone production runs completely unrestrained. Ketone levels frequently soar past 10 to 20+ mmol/L, entirely overwhelming the body's pH buffering systems and acidifying the blood.
To learn about what causes this condition, read our comprehensive guide on DKA Causes & Triggers. If you suspect you or a loved one is experiencing this emergency, view the critical red flags on our page for Recognizing Diabetic Ketoacidosis Symptoms.
Frequently Asked Questions (FAQ)
What is the primary cause of diabetic ketoacidosis?
The fundamental cause of DKA is a severe deficiency of functional insulin. Without enough insulin, the body cannot use blood sugar for energy and is forced to rapidly burn fat instead, creating a hazardous buildup of acidic ketones. This deficiency is most commonly triggered by missing insulin doses or experiencing systemic stress from an underlying illness or infection.
Can a person with Type 2 diabetes get ketoacidosis?
Yes, individuals with Type 2 diabetes can develop DKA, though it is less common than in Type 1 diabetes. It typically happens during periods of severe physiological illness (like a heart attack, stroke, or major infection) where stress hormones skyrocket and drastically overpower the body's remaining insulin. It is also seen as a side effect of certain oral diabetes medications known as SGLT2 inhibitors.
How fast can diabetic ketoacidosis develop?
DKA usually has a rapid onset, often materializing within 24 hours of severe insulin depletion or the onset of an acute underlying illness. Because it escalates so quickly into a life-threatening crisis, early intervention is vital.
Can you have ketoacidosis with normal blood sugar?
Yes, this is a medically recognized condition known as Euglycemic Diabetic Ketoacidosis (eDKA). In eDKA, a patient satisfies all the diagnostic criteria for ketoacidosis (acidic blood pH and high ketone levels) but their blood glucose remains near normal, typically under 200 mg/dL. This is most frequently associated with the use of SGLT2 inhibitor medications, pregnancy, prolonged fasting, or heavy alcohol consumption.