Learn how meglitinide diabetes medications like repaglinide and nateglinide manage post-meal blood sugar spikes. Explore benefits, doses, and safety notes.
Understanding Meglitinides (Glinides) for Type 2 Diabetes: A Fast-Acting Therapy
If your primary blood sugar challenge happens immediately after eating, your healthcare provider may evaluate a class of oral medications known as meglitinides (often called glinides). Unlike longer-acting baseline treatments, these drugs are explicitly designed to address rapid, post-meal glucose spikes (postprandial hyperglycemia).
What Are Meglitinides and How Do They Work?
Meglitinides are oral insulin secretagogues. Like sulfonylureas, their primary function is to trigger the release of insulin from the pancreatic beta cells. However, they achieve this through a highly distinct physiological profile.
The Mechanism of Action
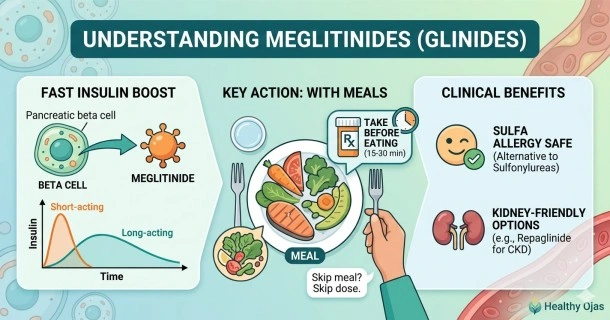
Meglitinides bind to specific receptors on the pancreatic beta cells to shut down ATP-dependent potassium channels, initiating insulin secretion. The key difference lies in their speed and duration: meglitinides have a much shorter metabolic half-life. They trigger a rapid, burst-like release of insulin that mimics the body’s natural response to food.
Because this insulin spike is short-lived—typically lasting only one to two hours—these medications must be taken strictly with meals (usually 15 to 30 minutes before eating). If you skip a meal, you must skip that corresponding dose of meglitinide to prevent blood sugar levels from dropping too low.
Common Types of Meglitinide Medications
There are two primary meglitinides widely utilized in modern clinical settings:
- Repaglinide (Common Brand names: Prandin, Gluconorm)
- Nateglinide (Common Brand name: Starlix)
Clinical Efficacy and Long-Term Results
Meglitinides are highly effective when targeted at individuals with robust post-meal glucose fluctuations. While short-term clinical metrics demonstrate an initial stabilizing effect, long-term therapeutic observations show significant efficacy:
- Repaglinide has been shown in long-term clinical trials to reduce overall HbA1c levels by 1.4% to 1.8% when optimized.
- Nateglinide tends to be slightly milder, typically lowering HbA1c by 0.4% to 0.6%, but offers a very rapid onset.
Glinides can be prescribed as a monotherapy or safely paired with other non-secretagogue diabetes therapies, including Metformin, Thiazolidinediones (TZDs), or Alpha-glucosidase inhibitors.
Key Clinical Benefits and Safety Profiles
Meglitinides fill a crucial niche for patients who may not tolerate other standard diabetes therapies:
- An Alternative for Sulfa Allergies: Because meglitinides are non-sulfonylurea agents, they are an excellent option for patients who require an insulin secretagogue but have a severe allergy to sulfa-based drugs.
- Lower Risk of Delayed Low Blood Sugar: Because the medication clears your system rapidly, it carries a lower risk of causing hypoglycemia during the late post-meal phase compared to traditional sulfonylureas.
- Kidney-Friendly Profiles (Repaglinide): Repaglinide is primarily metabolized and excreted via the liver and biliary pathway, with less than 10% cleared by the kidneys. This makes repaglinide a highly valuable, safer choice for individuals living with chronic kidney disease (CKD) who cannot take other oral agents.
Crucial Contraindications
Meglitinides are cleared by the liver and require careful medical titration. They should be used with caution, under strict medical oversight, in:
- Individuals with severe hepatic (liver) impairment.
- Pregnant or breastfeeding patients.
- Older adults who may have an increased sensitivity to rapid blood sugar shifts.
The specific dosing differences and titration limits between Repaglinide and Nateglinide.
Here is a clinical comparison table mapping out the typical dosing protocols, titration limits, and distinct parameters for both primary meglitinides based on standard clinical practices.
| Parameter | Repaglinide (Prandin, Gluconorm) | Nateglinide (Starlix) |
|---|---|---|
| Typical Starting Dose | • 0.5 mg before each meal (if A1C is close to target or patient is naive to therapy) • 1 mg to 2 mg before each meal (if baseline A1C is higher or switching from other secretagogues) | • 120 mg before each meal (standard initial dose) • 60 mg before each meal (may be considered if closer to A1C goals) |
| Dosing Frequency | Taken 15 to 30 minutes before main meals (usually 3 to 4 times daily, depending on eating frequency). | Taken 1 to 30 minutes before main meals (typically 3 times daily with breakfast, lunch, and dinner). |
| Titration Interval | Dosage adjustments are usually made at least one to two weeks apart based on post-meal blood glucose response. | Typically initiated at the target dose, but modifications can be evaluated after one to two weeks if needed. |
| Maximum Single Dose | 4 mg per meal. | 120 mg per meal. |
| Maximum Total Daily Dose | Do not exceed 16 mg per day. | Do not exceed 360 mg per day. |
| Missed Meal Protocol | Skip the meal, skip the dose. If a meal is omitted, the corresponding dose must be skipped to avoid hypoglycemia. | Skip the meal, skip the dose. The drug should only be taken if an active, carbohydrate-containing meal is consumed. |
Frequently Asked Questions (FAQ)
When exactly should I take my meglitinide medication?
You should take your meglitinide dose within 15 to 30 minutes before your first bite of a main meal. If you are sitting down for a meal and forgot to take it beforehand, you can take it during the meal. Never take a dose if you are skipping the meal entirely.
Can I take a meglitinide and a sulfonylurea together?
No. You should never combine a meglitinide (like repaglinide) with a sulfonylurea (like glipizide or glimepiride). Because both classes work via similar secretagogue mechanisms to stimulate the pancreas, combining them would not improve blood sugar control and would drastically increase your risk of severe hypoglycemia.
Why is repaglinide preferred over nateglinide for some patients?
Clinical data indicates that repaglinide provides a more robust overall reduction in both post-meal blood sugar spikes and baseline HbA1c levels compared to nateglinide. Additionally, repaglinide’s unique liver-cleared pathway makes it highly preferred for individuals with advanced kidney disease.
What are the main side effects of meglitinides?
The most common side effects are hypoglycemia (low blood sugar) and mild weight gain. Because meglitinides stimulate insulin production, they can cause your blood sugar to drop if your food intake doesn't match the timing of the dose. Symptoms of a drop include shakiness, sweating, and dizziness.