Confused by AMD options? Explore advanced treatments for dry and wet macular degeneration, from AREDS2 vitamins to complement inhibitors and anti-VEGF eye injections.
Advanced Macular Degeneration Treatments: Options for Dry and Wet AMD Explained
Age-related macular degeneration (AMD) treatment has evolved dramatically over the last decade, transitioning from limited observation strategies to highly targeted clinical therapies. While destroyed retinal tissue cannot be grown back, modern medical protocols focus intensely on slowing disease progression, protecting your remaining macula photoreceptors, and stabilizing or reclaiming functional central vision.
Because the underlying pathology varies significantly between the two forms of the disease, therapeutic approaches are divided into separate clinical paths.
1. Clinical Treatments for Dry Macular Degeneration (Atrophic AMD)
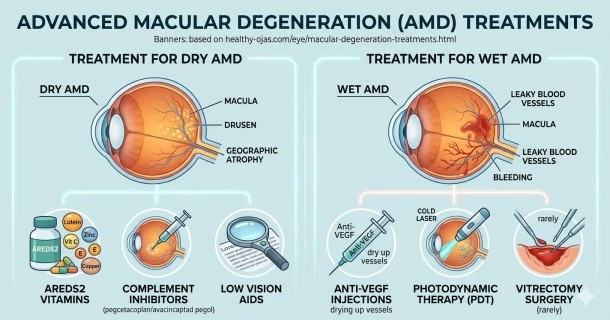
Dry AMD involves the gradual thinning of the macula cells and the accumulation of yellow waste deposits called drusen. Because tissue degradation is slow, treatments focus on cellular protection and metabolic support.
- Targeted Nutritional Supplements (The AREDS2 Formula): For individuals diagnosed with intermediate or late-stage dry AMD in one eye, high-dose specialized antioxidant vitamins are proven to reduce the risk of progressing to advanced vision loss by roughly 25%. The scientifically validated AREDS2 daily regimen consists of:
- Vitamin C (500 mg) and Vitamin E (400 IU)
- Zinc (80 mg as zinc oxide) and Copper (2 mg as cupric oxide to prevent zinc-induced anemia)
- Lutein (10 mg) and Zeaxanthin (2 mg) (Replacing beta-carotene to ensure safety for former and current smokers)
- Prescription Complement Inhibitor Injections: A groundbreaking class of FDA-approved medications—specifically pegcetacoplan and avacincaptad pegol—addresses geographic atrophy (advanced dry AMD). Injected directly into the vitreous fluid of the eye every 25 to 60 days, these therapies target and slow down the immune complement pathway responsible for destroying retinal cells.
- Low Vision Rehabilitation: Specially trained occupational therapists work closely with patients to optimize their peripheral field of vision. They implement high-contrast adaptive lighting, heavy-duty digital magnifiers, bioptic lenses, and audio-assisted technologies to restore daily independence.
2. Advanced Interventions for Wet Macular Degeneration (Neovascular AMD)
Wet AMD is characterized by abnormal, fragile blood vessels growing under the retina that leak fluid and blood. Left untreated, it causes rapid scarring and irreversible vision drop. Managing it requires direct, aggressive intervention.
- Anti-VEGF Injection Therapy: The absolute gold standard of care. Abnormal vessel growth is triggered by a chemical known as Vascular Endothelial Growth Factor (VEGF). Periodic eye injections of anti-VEGF medications—such as aflibercept, ranibizumab, faricimab, or bevacizumab—bind to this protein. This dries up existing fluid, causes leaky vessels to shrink, and prevents new ones from forming, frequently stabilizing or improving visual sharpness.
- Photodynamic Therapy (PDT): Less frequently used today but powerful in specific combination cases. An intravenous light-activated drug called verteporfin is infused into the arm, traveling directly to the eye's abnormal vessels. A specialized cold laser is then shone into the pupil, activating the chemical to seal the leaking vessels without harming the surrounding healthy retina.
- Surgical Interventions: In rare, severe instances where a massive subretinal hemorrhage occurs (heavy bleeding beneath the macula), vitreoretinal specialists may execute emergency surgeries—such as a vitrectomy combined with gas bubble placement or tissue plasminogen activator (tPA) injections—to physically displace or dissolve the blood before it destroys the photoreceptors.
Comparing Treatment Approaches: Dry vs. Wet AMD
| Clinical Metric | Dry AMD Management | Wet AMD Treatment |
| Primary Clinical Goal | Slowing cellular breakdown; delaying geographic atrophy. | Halting active fluid leakage; preventing subretinal macular scarring. |
| Primary Therapy Type | Targeted oral nutrition (AREDS2) & complement-inhibiting injections. | Intraocular anti-VEGF injections & occasional laser therapy. |
| Urgency Level | Ongoing monitoring; non-emergency. | High urgency; delays can lead to permanent central vision scarring. |
To understand the root causes behind these changes or learn how to identify warning signs early, visit our comprehensive resources detailing Macular Degeneration Causes, AMD Symptoms Guide, and Diagnostic Eye Tests Explained.
Frequently Asked Questions (FAQ)
Do anti-VEGF eye injections hurt?
The thought of an eye injection can be intimidating, but the procedure is highly tolerated and causes minimal discomfort. Before the injection, the eye is completely numbed using advanced topical anesthetic drops or a localized numbing gel. The eye is also thoroughly cleansed with an antiseptic solution to prevent infection. Most patients report feeling only a brief sensation of pressure rather than sharp pain.
Can I take standard over-the-counter multivitamins instead of AREDS2 supplements?
No, standard daily multivitamins do not contain the highly concentrated, specific ratios of antioxidants and minerals utilized in the clinical AREDS trials. Taking random doses or trying to match the formula with multiple separate over-the-counter bottles can result in dangerous nutritional imbalances or toxicities. Always use a verified AREDS2 formula recommended by your eye care professional.
How often will I need treatments for wet macular degeneration?
Anti-VEGF injections require long-term maintenance. Initially, injections are usually given every 4 weeks. As the leaking blood vessels stabilize, your ophthalmologist may employ a "treat-and-extend" protocol, gradually stretching the time between injections to 8, 12, or even 16 weeks based on how well your retina responds.