Discover how doctors accurately test for and diagnose narcolepsy using overnight polysomnography (PSG), multiple sleep latency tests (MSLT), and hypocretin spinal taps.
How is Narcolepsy Diagnosed?
Diagnosing narcolepsy requires a thorough clinical evaluation combined with objective, specialized sleep studies. Because its primary sign—severe daytime fatigue—is shared by many other conditions like clinical depression, sleep apnea, and chronic fatigue syndrome, narcolepsy is frequently misdiagnosed.
In school-aged children and teenagers, it is often misattributed to seizure disorders, behavioral problems, or learning difficulties. Due to its relative rarity, a proper diagnosis can take several years. A specialized diagnostic protocol is required to confirm the condition.
The Clinical Diagnostic Process
Before ordering lab assessments, a sleep specialist or neurologist will conduct a multi-step baseline medical evaluation:
- Detailed Clinical History: Documenting sleep patterns, the frequency of sudden sleep attacks, and looking for signs of cataplexy (sudden muscle weakness triggered by emotions). Cataplexy is a highly specific marker unique to Narcolepsy Type 1.
- Physical and Neurological Exam: Ruling out competing root causes of excessive fatigue, such as severe thyroid diseases, active infections, or substance use.
- Sleep Logs and Actigraphy: Patients are typically asked to keep a meticulous sleep diary or wear a wrist actigraph sensor for 1 to 2 weeks to prove they are maintaining adequate, regular sleep times prior to testing.
Gold-Standard Sleep Lab Diagnostics
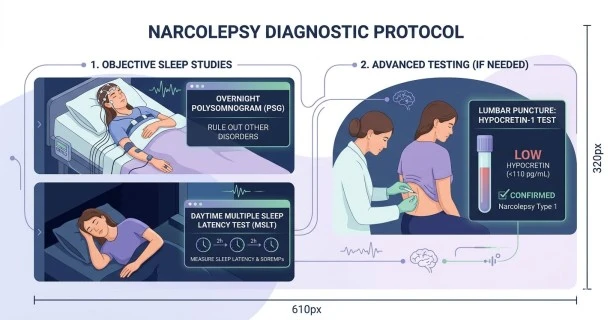
To objectively confirm a diagnosis of narcolepsy, patients must undergo two consecutive tests at an accredited sleep disorders center.
1. Overnight Polysomnogram (PSG)
The diagnostic process begins with an overnight Polysomnogram. This test tracks physiological changes across an entire night of sleep. Sensors record brain waves (EEG), rapid eye movements, muscle tension, heart rate, and breathing patterns. The PSG serves two vital clinical functions:
- Excluding Other Sleep Disorders: It rules out conditions like obstructive sleep apnea or periodic limb movement disorder that cause daytime exhaustion.
- Assessing Sleep Architecture: It checks if a patient displays fragmented nighttime sleep or transitions into an abnormal, immediate sleep-onset REM period (SOREMP) during the night.
2. Multiple Sleep Latency Test (MSLT)
Conducted the morning immediately following the PSG, the MSLT is the primary tool used to measure daytime sleepiness and REM tendency.
- The Procedure: The test consists of four to five scheduled nap opportunities spaced exactly two hours apart throughout the day. For each nap trial, the patient lies down in a dark, quiet room and is given 20 minutes to attempt to fall asleep while brain activity is monitored.
- Diagnostic Criteria for Narcolepsy: A diagnosis is strongly supported if the patient shows an average sleep latency of 8 minutes or less across the naps, combined with at least two Sleep Onset REM Periods (SOREMPs) during the testing protocol (an overnight SOREMP on the preceding PSG can count as one).
Advanced Biochemical Testing: The Hypocretin Test
In complex or ambiguous clinical cases—such as when a patient is unable to stop taking medications that alter REM sleep before an MSLT—a physician may perform a Hypocretin Test.
- The Procedure: A physician performs a lumbar puncture (spinal tap) by gently inserting a fine needle into the lower back to draw a small sample of cerebrospinal fluid (CSF).
- The Clinical Threshold: This sample is analyzed to measure the concentration of the wake-promoting neurotransmitter hypocretin-1 (orexin-A). A hypocretin level of 110 pg/mL or lower definitively confirms a diagnosis of Narcolepsy Type 1, even if daytime sleep studies are inconclusive.
Frequently Asked Questions (FAQs)
Why does it take so long to get an accurate narcolepsy diagnosis?
Narcolepsy is a relatively rare condition with symptoms that develop gradually. Its primary indicator, excessive daytime sleepiness, is easily confused with everyday exhaustion, depression, thyroid imbalances, or sleep apnea, often leading to years of misdiagnosis.
What should I expect during a Multiple Sleep Latency Test (MSLT)?
The MSLT is a full-day assessment consisting of 5 brief, scheduled nap opportunities spaced 2 hours apart. Brain wave sensors track exactly how long it takes you to fall asleep in a darkened room and check whether you enter REM dream sleep abnormally fast.
Can a regular blood test diagnose narcolepsy?
No, narcolepsy cannot be diagnosed through a standard blood test. While genetic testing can screen for the HLA-DQB1*06:02 marker to show a susceptibility to the condition, it cannot confirm the active disease. Objective sleep tests like a PSG and MSLT are required.
What is a SOREMP and why does it matter for diagnosis?
SOREMP stands for Sleep Onset REM Period. It occurs when an individual enters rapid eye movement (REM) sleep within 15 minutes of drifting off. Recording two or more SOREMPs during an MSLT is a strong clinical indicator of narcolepsy.
When is a lumbar puncture necessary for a narcolepsy diagnosis?
A lumbar puncture (spinal tap) is used when daytime sleep tests produce borderline or ambiguous results, or when a patient cannot safely discontinue medications (like antidepressants) that suppress REM sleep. It measures hypocretin levels directly in the spinal fluid to confirm Narcolepsy Type 1.